The 2026 Kidney Transplant Drug Coverage Cliff Medicare Beneficiaries Should Plan Around
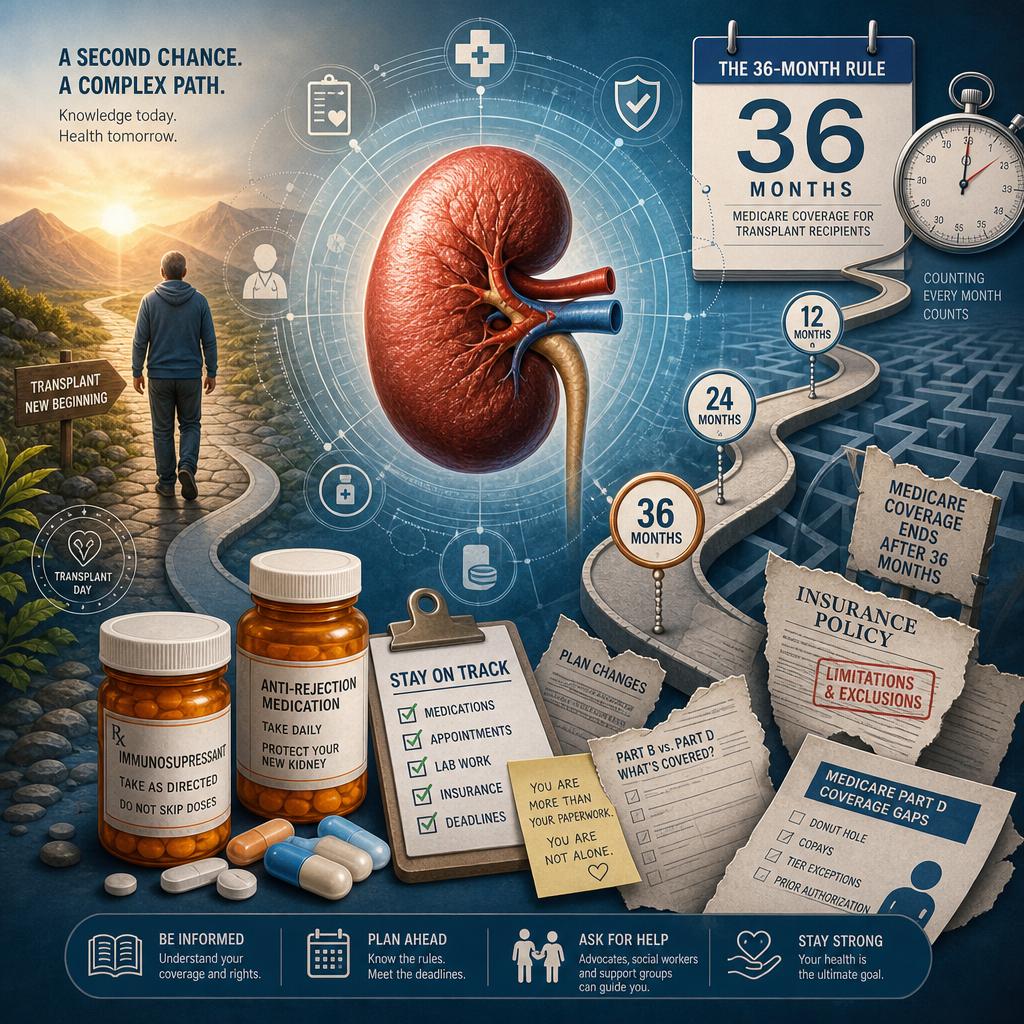
A kidney transplant is one of the most hopeful events in modern medicine. It can mean freedom from a dialysis schedule, fewer emergency interruptions, and a return to a life that feels less governed by lab values and treatment chairs. Yet in Medicare planning, that successful transplant can also introduce a quiet administrative deadline that many families do not see until a pharmacy claim fails.
The issue is especially important in 2026 for people whose Medicare eligibility began because of End Stage Renal Disease. Medicare states that if you are only eligible for Medicare because of ESRD and you receive a kidney transplant, your Medicare benefits end 36 months after the transplant . That sentence is easy to skim past, but it can determine whether the medication that protects the transplanted kidney is handled smoothly or becomes an urgent coverage problem.
The 36 Month Rule Is Not A Medical Deadline
The first mistake is assuming the 36 month rule is about whether the transplant is still medically fragile. It is not. Immunosuppressive therapy is often lifelong because the body can reject a transplanted organ long after the surgery itself. Medicare’s rule is about eligibility, not recovery. If a person has Medicare only because ESRD made them eligible, the successful transplant can eventually end the very Medicare coverage that helped support the treatment path.
This is where the coverage conversation becomes more technical than most brochures suggest. Medicare covers immunosuppressive drugs when Medicare paid for the organ transplant, but the beneficiary generally must have had Part A at the time of the covered transplant and must have Part B when receiving the immunosuppressive drugs, unless they qualify for the separate immunosuppressive drug benefit . In real life, that means the coverage chain has several links: the transplant payment history, the timing of Part A, the status of Part B, and whether another payer has stepped in.
Why Part B And Part D Can Feel Like Two Different Pharmacies
Families often hear the phrase drug coverage and think of Part D. That is understandable, especially in 2026, when Medicare drug coverage has a major consumer protection: covered Part D drug out of pocket costs are capped at $2,100 for the year, after which the beneficiary pays no copayment or coinsurance for covered Part D drugs for the rest of the calendar year . That cap is meaningful, but it does not automatically answer the immunosuppressive drug question.
The reason is that immunosuppressive drugs may be Part B drugs if Medicare paid for the transplant and the coverage conditions are met. If Part B does not cover them, Medicare drug coverage may cover them under Part D . That distinction matters because Part B and Part D have different billing systems, different pharmacy workflows, different appeal routes, and different cost structures. A beneficiary who has been stable on a transplant medication for years can still run into trouble if the pharmacy, plan, or provider treats the drug under the wrong benefit.
The Separate Immunosuppressive Drug Benefit Is Narrow By Design
Medicare does offer a special benefit for certain kidney transplant recipients after the 36 month ESRD Medicare period ends. The handbook describes it as a benefit that helps pay for immunosuppressive drugs beyond 36 months when the beneficiary does not have certain other coverage, such as a group health plan, TRICARE, or Medicaid that covers those drugs . That sounds reassuring, but the scope is deliberately limited.
This benefit only covers immunosuppressive drugs, including certain compounded immunosuppressive drugs, and no other items or services. Medicare is explicit that it is not a substitute for full health coverage . That means it may help keep the anti rejection medication accessible, but it will not cover the broader medical needs that often accompany transplant life, such as specialist visits, hospital care, imaging, infection workups, diabetes management, cancer surveillance, or other prescriptions not covered by the benefit.
For someone who is 48, received Medicare solely because of ESRD, and then had a kidney transplant in 2023, 2026 may be the year the family needs to map the next coverage layer. The question is not simply, will Medicare pay for the pills. The better question is, what happens to the entire health insurance architecture when ESRD based Medicare ends, and is the immunosuppressive drug benefit only a bridge for one category of medication.
Medicare Advantage Requires A Network Review Before The Surgery Path Changes
Medicare Advantage can be a strong fit for some beneficiaries, but transplant related planning requires a deeper review than checking the premium and dental allowance. Medicare tells beneficiaries who are on a transplant waiting list or believe they may need a transplant to check with a Medicare Advantage plan before joining, including whether doctors, hospitals, and other providers are in network, how covered drugs are treated, prior authorization rules, and coverage for living donors . That is not a casual suggestion. It is a sign that transplant care is network sensitive.
A transplant program may involve a center of excellence, a nephrologist, a surgeon, a pharmacy familiar with anti rejection protocols, and rapid coordination when lab results change. If a plan’s network does not include the right transplant center, or if a medication requires prior authorization that is not prepared in advance, the beneficiary may experience delays that feel clinical but began as benefit design issues. Medicare Advantage plans must cover medically necessary services covered by Original Medicare, but they may require prior authorization for certain services or supplies .
The One List A Transplant Household Should Build Before 2026
Because this topic is so fact dependent, a transplant household should not rely on memory or assumptions. Before the 2026 plan year begins, gather one working file with the essential proof points:
- The transplant date, the transplant facility, and whether Medicare paid for the covered transplant.
- Current Medicare eligibility basis, including whether Medicare is based only on ESRD or also on age or disability.
- Active Parts A, B, C, and D status, plus any employer, union, Medicaid, TRICARE, or Marketplace coverage.
- A current medication list showing each immunosuppressive drug, dosage, pharmacy, prescriber, and whether the drug is billed under Part B or Part D.
- Any prior authorization approvals, exception letters, plan notices, and pharmacy denial notices.
That list is not busywork. It is the difference between an orderly review and a crisis response at the counter. Plans can have coverage rules for certain drugs, including prior authorization, quantity limits, and step therapy . If the medication is moving through Part D rather than Part B, those plan rules can determine whether the refill is routine or contested.
Why The 2026 Part D Cap Helps But Does Not Solve Everything
The $2,100 Part D out of pocket cap is one of the most important Medicare drug protections for 2026. But transplant beneficiaries should be careful not to overread it. The cap applies to covered Part D drugs, and actual drug costs can vary based on whether prescriptions are on the formulary, what tier they are placed in, the benefit phase, the pharmacy used, and whether the person receives Extra Help .
That means the cap is not a guarantee that every transplant medication will be covered without friction. A drug not on the formulary may require an exception. A plan may require the prescriber to show medical necessity before coverage. A pharmacy may process a claim under Part D when the facts support Part B, or the reverse. These are not theoretical problems. They are the kinds of misrouting issues that a knowledgeable broker looks for before a beneficiary is standing at the pharmacy with a limited supply remaining.
Professional Guidance Turns A Coverage Cliff Into A Plan
The most important takeaway for 2026 is that kidney transplant drug coverage is not a single yes or no question. It is a sequence: why you have Medicare, when the transplant occurred, whether the 36 month ESRD clock applies, whether Part B or Part D should pay, whether another payer changes eligibility for the special immunosuppressive drug benefit, and whether your doctors and pharmacy can actually operate inside the plan you choose.
Vista Mutual Insurance Services helps clients slow this process down and examine each moving part before it becomes urgent. For a transplant recipient, peace of mind is not just having a card in the wallet. It is knowing that the plan, pharmacy, prescriber, and Medicare rules are aligned before the next refill, the next lab result, or the next annual enrollment decision. If your household is approaching the 36 month mark or you want a second set of eyes on your 2026 coverage, Schedule your 2026 Medicare consultation with Vista Mutual.