The 2026 Medicare Care Compare Decision Before You Choose A Facility
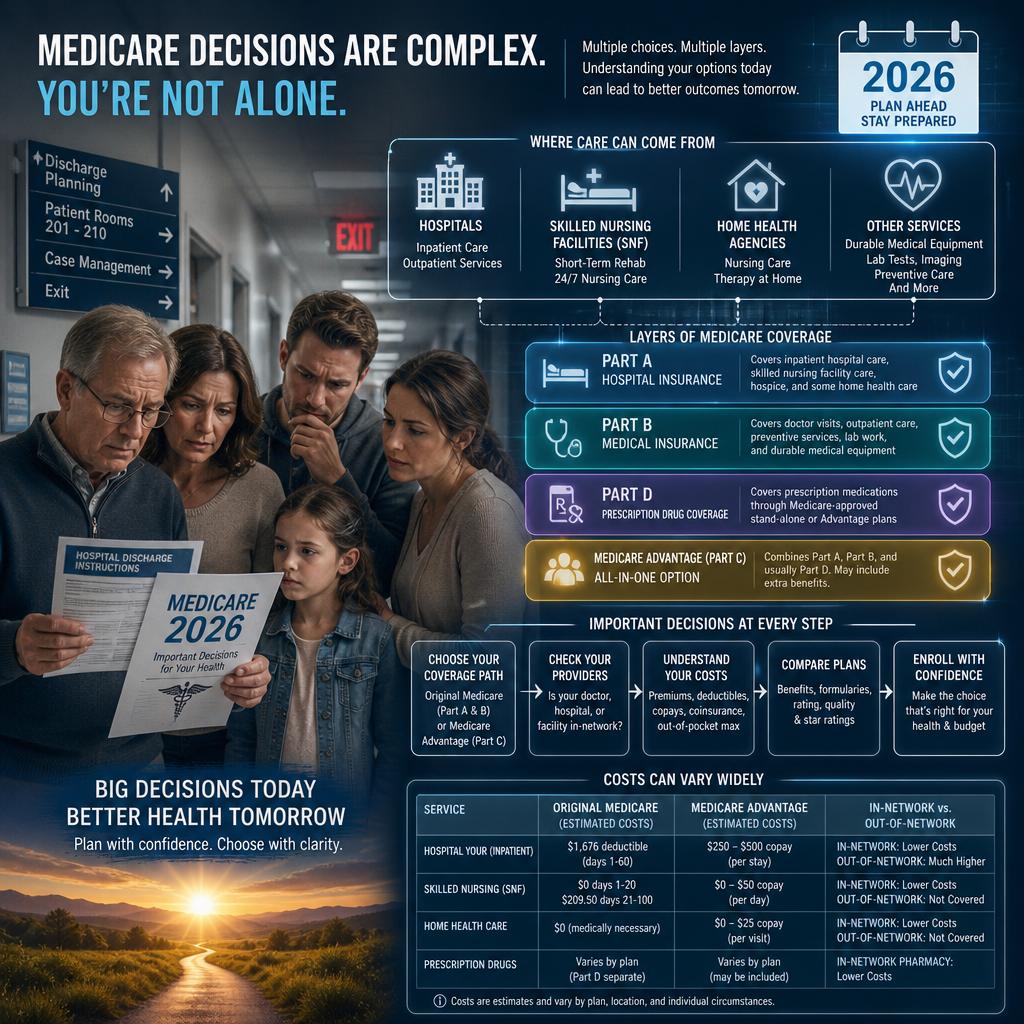
A Medicare choice often looks simple until a family is standing in a hallway with discharge papers in hand. A spouse is told that home health can start tomorrow, a daughter is handed a list of skilled nursing facilities, or a patient with a planned procedure is asked which hospital they prefer. The name that sounds familiar is not always the provider that fits the coverage, the clinical need, or the financial exposure.
That is why one of the most practical 2026 Medicare planning tools is not a glossy plan brochure. It is Medicare Care Compare, used with professional interpretation. Medicare points beneficiaries to Care Compare to find and compare providers, hospitals, and facilities, and the 2026 handbook also explains that Original Medicare generally lets you use any Medicare enrolled provider or facility that accepts Medicare patients anywhere in the United States . That freedom is valuable, but it can also create a false sense of safety. Being able to go somewhere does not mean every cost, status issue, supplier relationship, or follow up service will unfold the way you expect.
Care Compare Is A Starting Point Not A Coverage Decision
Care Compare can help a family identify Medicare approved providers, but it does not replace the deeper question: how will this specific Medicare setup pay for this specific episode of care? A beneficiary in Original Medicare may be focused on whether the hospital takes Medicare. A beneficiary in a Medicare Advantage plan must also ask whether the facility, physicians, suppliers, and post acute providers are in network, whether a referral is required, and whether prior authorization applies. Medicare’s 2026 materials make that distinction clear: Original Medicare usually does not require approval before services or supplies are covered, while Medicare Advantage plans may require prior authorization .
Consider a 72 year old man planning a knee replacement in 2026. His surgeon may operate at three facilities. Care Compare may show useful quality signals, but the insurance question is layered. Under Original Medicare, the patient may owe coinsurance unless he has Medigap or other secondary coverage. Under Medicare Advantage, the better rated facility might be outside the plan network, or the hospital may be in network while the rehabilitation provider is not. The mistake is assuming that quality comparison and coverage confirmation are the same exercise.
The Post Acute Choice Can Be Where The Bill Changes
The most stressful Medicare decisions often happen after the acute medical event, not before it. A patient is discharged from the hospital and the family hears phrases like skilled nursing, inpatient rehabilitation, home health, outpatient therapy, or hospice. Each path carries different rules, and Care Compare can help locate providers, but it cannot decide which benefit category applies.
The difference matters because Medicare coverage is built around precise eligibility tests. Skilled nursing facility care, for example, generally requires a three day minimum medically necessary inpatient hospital stay, not counting the day of discharge, and the patient must need daily skilled care that can practically be provided only as a skilled nursing facility inpatient . Medicare also notes that some Accountable Care Organizations may allow skilled nursing facility care without the usual three day hospital stay if other conditions are met . That one detail can completely change the recovery plan.
Home health has its own rules. Medicare covers medically necessary part time or intermittent skilled nursing care, therapy, and certain related services, but a clinician must assess the patient face to face, a provider must order the care, and a Medicare certified home health agency must provide it. The beneficiary must also be homebound under Medicare’s definition . A high quality home health agency on Care Compare is still not enough if the order, certification, homebound status, or plan authorization is missing.
The Hidden Problem Is That Providers Do Not All Sit In The Same Payment Box
Families often think of a facility as one bill. Medicare rarely works that way. A hospital stay may involve the facility, hospital employed clinicians, outside specialists, imaging providers, durable medical equipment suppliers, home health agencies, pharmacies, and rehabilitation partners. In Original Medicare, assignment is a critical protection because it means the provider or supplier accepts the Medicare approved amount as payment in full and does not bill more than the deductible and coinsurance . In Medicare Advantage, the key issue may be whether each provider belongs to the plan’s network and whether the plan has approved the service.
This is where Care Compare becomes a professional planning tool rather than a casual search box. A beneficiary recovering from a fall might need a hospital bed, walker, home health nursing, and follow up imaging. Medicare covers medically necessary durable medical equipment when ordered by a Medicare enrolled provider for home use, but the beneficiary generally pays 20 percent of the Medicare approved amount, and the supplier assignment question can affect whether the patient is asked to pay the full cost upfront before Medicare later reimburses its share . A family that only checked the hospital may miss the supplier problem entirely.
The same is true for diagnostic tests. Medicare covers X rays, MRIs, CT scans, EKGs, and certain other diagnostic tests, but hospital outpatient testing can bring a separate copayment, and Medicare only pays for certain advanced diagnostic tests if they are performed by an accredited provider . In a real 2026 scenario, the question is not simply whether an MRI is covered. It is where it is performed, who bills it, whether the provider is accredited, whether the plan authorized it, and whether a hospital outpatient setting changes the patient’s share.
The One List To Use Before You Say Yes To A Facility
Before choosing a hospital, skilled nursing facility, home health agency, hospice, dialysis facility, imaging center, or supplier in 2026, ask these questions in one sitting: Is the provider Medicare enrolled or Medicare certified where required, does it accept assignment if I am in Original Medicare, is it in network if I am in Medicare Advantage, does my plan require prior authorization, will separate physicians or suppliers bill me, what benefit category will Medicare use, and what happens if my care setting changes after admission?
That final question deserves attention. Medicare explains that inpatient versus outpatient status affects what you pay and whether you qualify for Part A skilled nursing facility care. A patient is an inpatient only when the hospital formally admits the patient with a doctor’s order, and a person can be an outpatient even after spending the night in the hospital for observation, tests, or emergency services . Care Compare may help you choose a facility, but it will not protect you from misunderstanding your status once you are inside that facility.
Medicare Advantage Makes The Search More Local And More Conditional
For Medicare Advantage members, the Care Compare decision should be paired with a plan specific verification. Medicare explains that Advantage plans may require members to use doctors and other providers in the plan network and service area for non emergency care, and some plans cover out of network non emergency care only at higher cost . That means a facility can be excellent, Medicare participating, and still financially impractical for a particular plan member.
The 2026 handbook also reminds beneficiaries that Advantage plans have annual limits on what members pay for covered Part A and Part B services, while Original Medicare has no yearly out of pocket limit unless the person has supplemental coverage such as Medigap, Medicaid, employer, retiree, or union coverage . Prescription drugs are a separate analysis: Part D out of pocket costs for covered drugs are capped at $2,100 in 2026, but that cap does not erase medical cost sharing for hospitals, therapy, imaging, or durable medical equipment . This separation is one of the reasons Medicare planning feels so disorienting to families who are otherwise financially sophisticated.
The practical takeaway is that provider choice should not begin when a crisis begins. If you have a surgery scheduled, a chronic condition that may require dialysis, a serious diagnosis that could involve home infusion, or a spouse likely to need post acute care, the best time to map facilities is before the order is written. Once the discharge planner is moving quickly, your options may narrow to the providers that can accept the patient immediately, not necessarily the ones that best fit your coverage strategy.
A Better Way To Choose Before The Hospital Chooses For You
The most effective Medicare planning in 2026 combines three layers: the public quality tools, the official Medicare coverage rules, and the actual plan documents that govern your costs and access. Care Compare can show possibilities. Your Evidence of Coverage, provider directory, formulary, authorization rules, and supplemental coverage reveal whether those possibilities are practical.
Vista Mutual helps clients turn that maze into a working plan. We look beyond the premium and ask how your coverage behaves when you need a facility, a specialist, a supplier, a drug, or a recovery setting. If you want confidence before a hospitalization, surgery, discharge, or annual plan decision, Schedule your 2026 Medicare consultation. The peace of mind comes from knowing not just where you can receive care, but how your Medicare coverage is likely to respond when it matters.