The 2026 Medicare Chemotherapy Setting Test Cancer Patients Should Price Before Treatment Starts
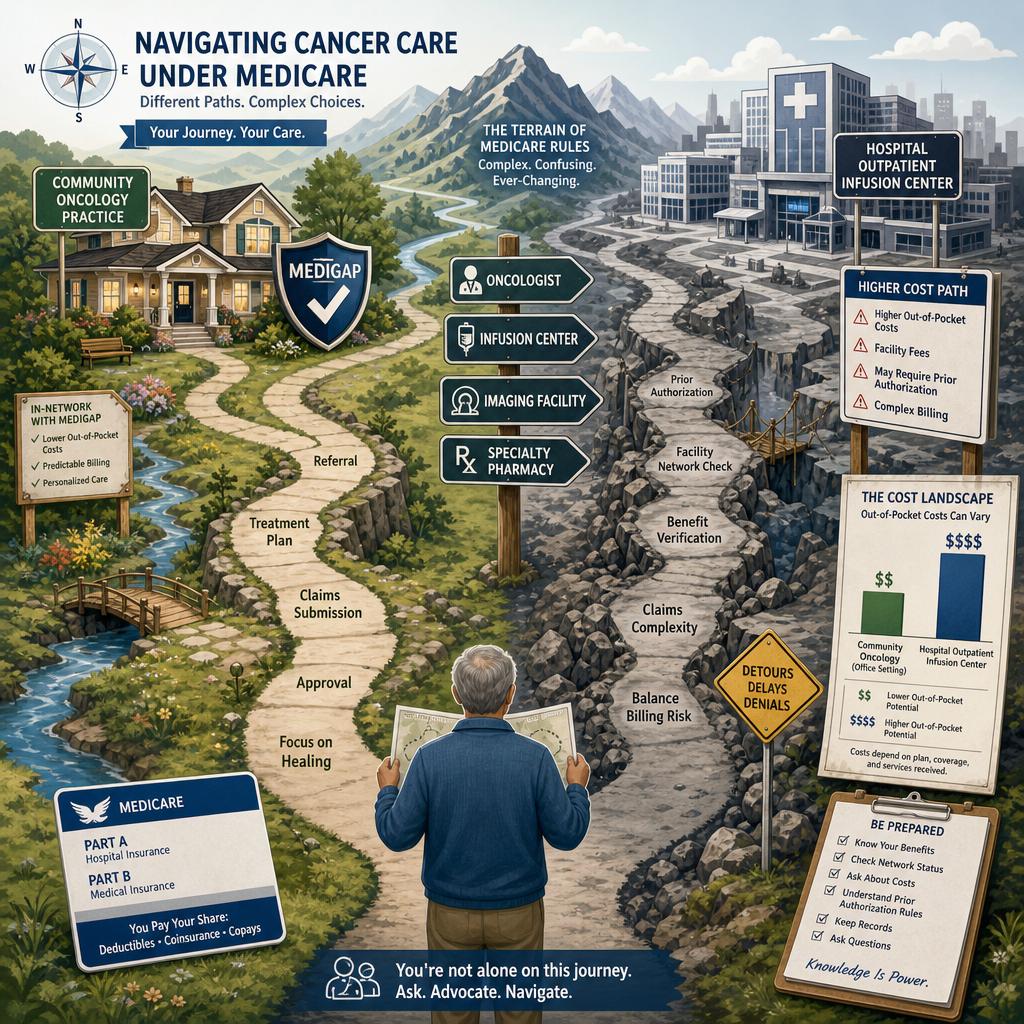
A cancer diagnosis makes Medicare feel less like insurance and more like terrain. Families quickly learn the names of oncologists, infusion centers, imaging facilities, specialty pharmacies, and hospital departments, often before they have had time to understand which part of Medicare is actually paying the bill. In 2026, one of the most important questions is not only whether chemotherapy is covered. It is where the chemotherapy is being delivered.
Consider a beneficiary named Elaine who has Original Medicare and a Medigap policy, and her neighbor Robert who chose a Medicare Advantage plan with a low premium and drug coverage. Both are told they need the same cancer drug. Elaine receives it in an oncology practice owned by a physician group. Robert is referred to a hospital outpatient infusion department. The medication sounds identical, the treatment intent is identical, and the calendar looks identical. Yet their bills, authorizations, network requirements, and appeal rights may not look identical at all.
Why Chemotherapy Is Usually A Part B Conversation Not A Part D One
Many people now associate Medicare drug costs with the 2026 Part D out of pocket cap, and understandably so. Medicare states that yearly out of pocket costs for covered Part D drugs are capped at $2,100 in 2026, after which the beneficiary pays no copayment or coinsurance for covered Part D drugs for the rest of the calendar year . That is a major protection for retail and mail order prescriptions covered by a drug plan.
But many chemotherapy drugs are not handled like pills picked up at a pharmacy counter. When cancer drugs are infused or injected by a clinician in a medical setting, they are often billed under Part B rather than Part D. Medicare describes chemotherapy coverage across a doctor office, freestanding clinic, or hospital outpatient setting when the beneficiary has cancer, with the cost sharing depending on the site of care . This is the first insider distinction families need to understand: the $2,100 Part D cap does not automatically protect you from every medication used in cancer treatment.
The Same Treatment Can Produce A Different Bill In A Different Room
Medicare’s 2026 handbook makes the setting distinction plain. If chemotherapy is furnished in a doctor office or freestanding clinic, the beneficiary pays 20% of the Medicare approved amount, and the Part B deductible applies . If chemotherapy is furnished in a hospital outpatient setting, the beneficiary pays a copayment for chemotherapy in that setting . That difference can matter because hospital outpatient billing often brings a facility structure that feels very different from a community oncology office.
For someone with Original Medicare and a comprehensive Medigap policy, the practical impact may be softened because the supplement may pay some or all of the Part B coinsurance depending on the plan. For someone without supplemental coverage, the 20% exposure can be substantial because Original Medicare generally has no yearly out of pocket limit unless the person has other coverage such as Medigap, Medicaid, employer, retiree, or union coverage . A Medicare Advantage enrollee has a different protection: the plan must have a yearly limit on what the member pays for covered Part A and Part B services, and once that limit is reached, the member pays nothing for covered services for the rest of the year . That does not mean the path is simpler. It means the risk is shaped differently.
Medicare Advantage Adds A Second Test Before Treatment Begins
In a Medicare Advantage plan, the question is not only what Medicare covers in theory. The patient also needs to know whether the oncologist, infusion site, hospital, imaging center, and pharmacy pathway are inside the plan’s rules. Medicare Advantage plans must cover medically necessary services covered by Original Medicare, but Medicare also warns that beneficiaries may need plan approval, often called prior authorization, before certain services or supplies are covered .
This can create an uncomfortable timing problem after a diagnosis. The oncologist may be ready to begin treatment, but the plan may need to confirm medical necessity, drug selection, setting, dose, or network status. Medicare Advantage plans also use different cost sharing structures, and Medicare notes that a member’s costs depend on factors such as premiums, deductibles, copayments, coinsurance, the type and frequency of care, whether services are in network, and whether the plan offers extra benefits . For chemotherapy specifically, there is one important protection: Medicare says Medicare Advantage plans cannot charge more than Original Medicare for certain services, including chemotherapy, dialysis, and days 21 through 100 of skilled nursing facility care . That protection is meaningful, but it does not eliminate network management, authorization delays, or the need to verify the infusion location.
The Assignment Rule Can Protect The Drug But Not Every Surprise
For Part B covered drugs, Medicare includes a safeguard that many beneficiaries never hear about until they are already reviewing statements. Doctors and pharmacies must accept assignment for Part B covered drugs, meaning the patient should not be asked to pay more than the applicable coinsurance or copayment for the Part B drug itself . That rule is important because cancer drugs can be expensive, and assignment prevents balance billing on the drug beyond the Medicare approved structure.
Still, assignment is not the same as a full cost estimate. A cancer visit can involve the physician service, drug administration, lab monitoring, imaging, anti nausea medications, port care, supplies, and facility charges. Medicare also explains that when Part B covered drugs are received in a hospital outpatient setting as part of outpatient services, the patient may pay a copayment for the services, and Part B does not cover self administered drugs in a hospital outpatient setting . This is why a beneficiary can be told that chemotherapy is covered and still receive multiple bills from different entities after the same day of care.
The Pre Treatment Questions That Separate Planning From Guessing
Before treatment begins, the most valuable conversation is often not about whether Medicare covers cancer care. It is about which billing pathway each piece of care will use. A high quality Medicare review should connect the oncologist’s treatment plan to the insurance design before claims start moving.
The patient or caregiver should ask these questions before the first infusion:
- Will each cancer drug be billed under Part B or Part D, and does the $2,100 Part D cap apply to any of them in 2026?
- Is the infusion site a doctor office, freestanding clinic, hospital outpatient department, or inpatient hospital setting?
- If enrolled in Medicare Advantage, are the oncologist, infusion center, hospital, lab, and imaging providers all in network?
- Does the plan require prior authorization or an organization determination before the drug, site of care, or regimen is approved?
- If using Original Medicare, is there a Medigap, retiree, union, Medicaid, or other secondary payer that will help with the Part B deductible and coinsurance?
These questions are not administrative trivia. They are the difference between walking into treatment with a realistic financial map and discovering the rules after the claims have already been processed.
A Better 2026 Plan Starts Before Treatment Begins
The hardest Medicare problems often arise when a medically correct treatment plan collides with an unexamined insurance structure. Cancer care is one of the clearest examples. The clinical team may be focused on the best regimen, while the insurance system is quietly sorting each service into Part A, Part B, Part D, Medicare Advantage medical coverage, network rules, prior authorization, and supplemental coverage.
That is why professional guidance is not merely helpful during annual enrollment. It can be decisive when health changes. Vista Mutual Insurance Services helps beneficiaries compare Medicare Advantage, Medicare Supplement, and Part D strategies through the lens of real medical use, not just premiums and brochures. If 2026 may bring cancer treatment, infusion therapy, specialist care, or a major change in prescriptions, Consult with the Vista Mutual team before the first bill teaches you what your plan really means.